Материал: 100_Cases_in_Clinical_Medicine
This page intentionally left blank
CASE 99: SHORTNESS OF BREATH
History
A 50-year-old woman has complained of shortness of breath for 3 months. It has steadily become more severe and is associated with an occasional cough. Otherwise she has been well. She smokes 15 cigarettes per day and drinks about 14 units of alcohol each week. Her 20-year-old son has asthma and she has tried his salbutamol inhaler on two or three occasions but found it to be of no real benefit. She has tested herself on her son’s peak flow meter at home and she has obtained values of about 100 L/min. On direct questioning she says that the shortness of breath tends to be worse on lying down but there are no other particular precipitating factors or variations through the day. She works as an office cleaner and has no significant previous medical history.
Examination
Her respiratory rate is 18 per minute. Pulse rate is 72/min and blood pressure 138/84 mmHg. The heart sounds are normal. There is a generalized wheeze heard all over the chest but no other abnormalities.
INVESTIGATIONS
The chest X-ray is normal and respiratory function tests are performed (Figs 99.1 and 99.2). Results are as follows:
|
Actual |
Post-bronchodilator |
Predicted |
FEV1 (L) |
1.20 |
1.20 |
3.5–4.3 |
FVC (L) |
4.10 |
4.1 |
4.6–5.4 |
FER (FEV1/FVC) (%) |
29 |
29 |
72–80 |
PEF (L/min) |
80 |
80 |
440–540 |
Residual volume (L) |
1.8 |
1.8 |
1.6–2.8 |
Total lung capacity (L) |
5.9 |
5.9 |
5.1–7.0 |
FEV1: forced expiratory volume in 1 s; FVC, forced vital capacity; FER, forced expiratory ratio; PEF, peak expiratory flow.
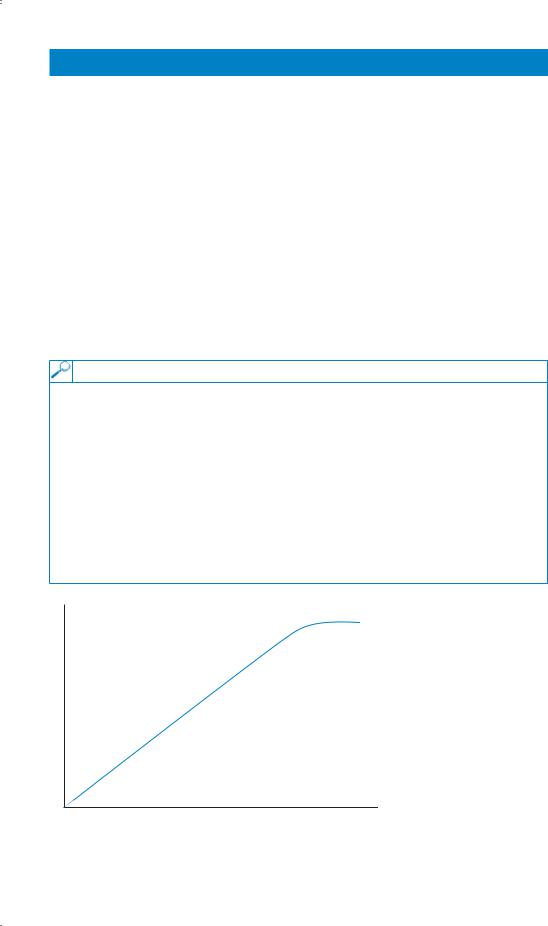
Expiratory flow
Volume
Time |
Figure 99.1 Spirometry. |
250
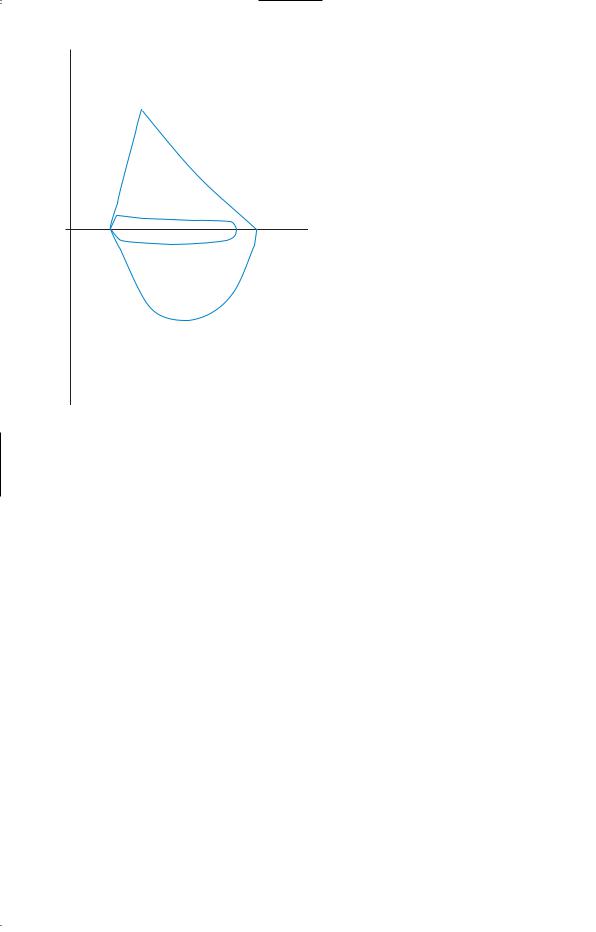
Flow
Volume
Figure 99.2 Flow–volume loop.
Question
• What do these findings indicate?
251
ANSWER 99
The flow–volume curve shows the same low flow throughout the whole volume of the vital capacity. It is similar in both inspiration and expiration as shown in the flow volume loop (Fig. 99.2). This situation is typical of a rigid large-airway obstruction. It is not reversible with bronchodilator therapy. The spirometry trace of volume against time in such cases shows a straight line of the same reduced flow right up to the vital capacity. These findings are typical of a narrowing in a larger airway. On examination, this airway narrowing is likely to produce a single monophonic wheeze which may be heard over a wide area of the chest.
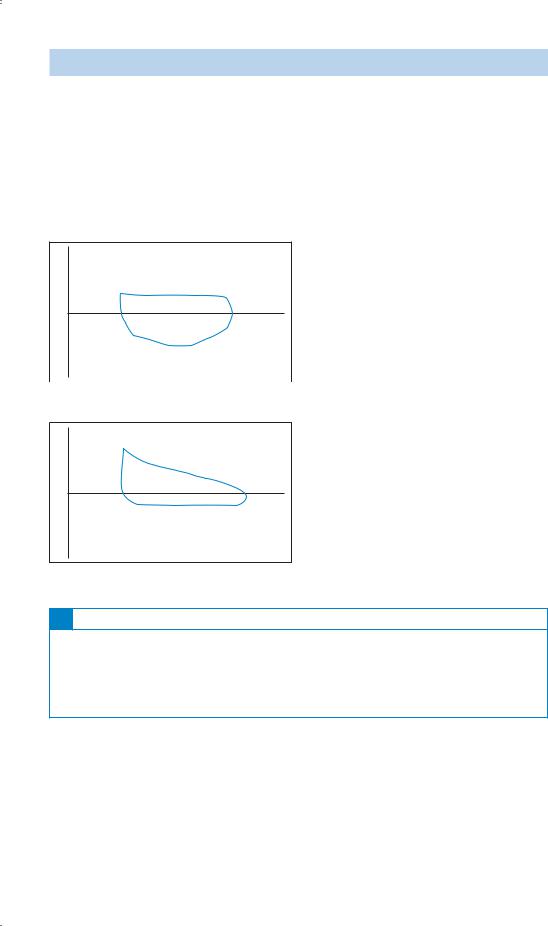
Flow
Flow
Volume
Figure 99.3 Flow–volume loop: intrathoracic narrowing.
Volume
Figure 99.4 Flow–volume loop: extrathoracic narrowing.
!Differential diagnosis of rigid large-airway obstruction
The situation may easily be confused with asthma if the peak flow and the wheezing are accepted uncritically. In asthma, the spirometry will show a reduced FEV1 but the flow rate (and therefore the slope of the line relating volume and time) will vary. The wheezing in asthma comes from many narrowed airways of different calibre and mass, and the wheezes are often described as polyphonic.
The fixed flow in inspiration and expiration in this case suggest a rigid large-airway narrowing. If the narrowing can vary a little with pressure changes, then the pattern will depend on the site of the narrowing (Figs 99.3 and 99.4). If it is outside the thoracic cage, as in a laryngeal lesion, it will be more evident on inspiration. If the site is intrathoracic, the flow limitation will be greater in expiration. Large-airway narrowing can be caused by inflammatory conditions such as tuberculosis or Wegener’s granulomatosis, damage from prolonged endotracheal intubation or by extrinsic pressure such as a retrosternal goitre. However, the commonest cause is a carcinoma of a large airway.
252
Some further investigation of the large airways is required. The great majority of symptomatic lung tumours are visible on plain chest X-ray but central lesions in large airways may not be seen. Further investigation could be a bronchoscopy or a computed tomography (CT) scan. A bronchoscopy to see and biopsy any lesion would be best. In this case, fibre-optic bronchoscopy showed a carcinoma in the lower trachea reducing the lumen to a small orifice. Treatment was by radiotherapy with oral steroids to cover any initial swelling of the tumour which might increase the degree of obstruction in the trachea.
KEY POINTS
•Large-airway narrowing produces characteristic findings on visual displays of respiratory function but is more difficult to identify from the numbers alone.
•A small proportion of central lung tumours may present with local symptoms but a normal chest X-ray.
253